Guides
What a new chiropractic practice needs to bill Medicare
Before billing Medicare, a new chiropractic practice needs an NPI, Medicare enrollment, the three CMT codes, the AT modifier and a sound treatment plan.
What to take away
- Medicare pays for manual manipulation of the spine to correct a subluxation, and only when the claim carries the AT modifier and the record supports medical necessity.
- Before the first claim, the chiropractor needs an NPI, a completed Medicare enrollment and contact with the practice's Medicare Administrative Contractor (MAC).
- The treatment plan is the document that decides the claimit must state the subluxation, the planned visit count, and the objective measure used to judge progress.
- Covered visits carry normal Part B cost sharingthe deductible applies first, then coinsurance on the Medicare-approved amount.
- Documentation gaps, not the adjustment itself, are the common cause of denial and recoupment.
- Confirm current requirements with your MAC, your state board, and a certified coder before you bill.
Before the first Medicare claim
CMS sets out enrollment in four steps for practitioners who want to bill Medicare. First, get a National Provider Identifier (NPI), which is issued through the National Plan and Provider Enumeration System (NPPES). Second, complete the Medicare enrollment application in PECOS, the online Medicare enrollment system; a paper application, Form CMS-855I for physicians and non-physician practitioners, is the fallback when online filing is not possible. Third, pay the Medicare application fee if it applies. Fourth, work with your MAC, which is specific to the region where you practice and may ask for more information while it processes the application.
Once enrolled, the practice must report a change in ownership, an adverse legal action or a change in practice location within 30 days, and all other changes within 90 days, or risk having its Medicare billing privileges revoked. The licence comes first: Medicare covers manipulation only where the treatment is legal in the state where it is performed, so the state board's licence and scope rules sit underneath every claim.
What Medicare actually covers
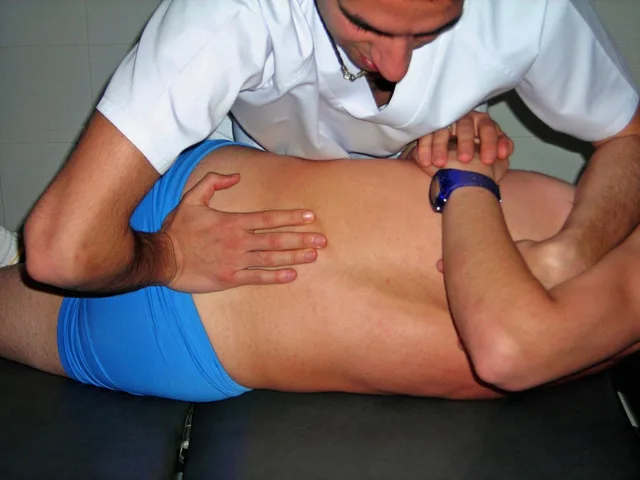
Medicare's chiropractic benefit is narrow. It covers manual manipulation of the spine to correct a subluxation, and nothing else in the chiropractic scope. X-rays, massage, ultrasound, and extremity adjustment are not covered under this benefit, whatever a practice's own fee schedule lists.
Medicare covers vs not covered
Covered
- Manual manipulation
- Yes
- Subluxation correction
- Yes
- X-rays
- No
- Massage
- No
- Ultrasound
- No
- Extremity adjustment
- No
Not covered
- Manual manipulation
- No
- Subluxation correction
- No
- X-rays
- Yes
- Massage
- Yes
- Ultrasound
- Yes
- Extremity adjustment
- Yes
That means a new owner's first compliance decision is not a policy binder. It is deciding which services go on a Medicare claim and which go to a cash or self-pay agreement.
The claim itself uses a short list of codes. CMS's MLN Matters article on chiropractic coverage states that doctors of chiropractic are limited to billing three CPT codes under Medicare: 98940 for one to two spinal regions, 98941 for three to four regions, and 98942 for five regions. The same article ties the precise level of the subluxation to the claim and lists the subluxation diagnosis codes by area of the spine, in the ICD-10 M99.0 range.
The AT modifier is the claim's signal that the visit was active treatment rather than maintenance. Maintenance therapy is not covered. If your record cannot show why a visit was active, the modifier will not save it.
The treatment plan is the claim
CMS states that coverage depends on documentation supporting medical necessity, and that insufficient documentation can lead to denial. In practice the treatment plan carries that weight.
What a defensible plan names
- The subluxation
- The spinal level
- Planned number of visits
- Objective measure for improvement
- Same measure recorded each visit
- Comparison showing change since last visit
A plan that holds up names the subluxation, the level, the planned number of visits, and the objective measure you will use to decide whether the patient is improving. Range of motion, a pain scale, or a functional score all work if you record the same measure each visit.
The subsequent-visit note then has one job: show what changed since the last visit and why another active visit was warranted. A note that repeats the initial findings without a comparison reads as maintenance. CMS treats care as maintenance when further clinical improvement cannot reasonably be expected and the treatment becomes supportive rather than corrective.
Where new practices lose money
Denials in a new chiropractic office usually trace to four places.
- The treatment plan is written once and never updated when the visit count runs out.
- The AT modifier is applied to every claim on a schedule rather than per visit.
- The patient is told Medicare will pay 80 percent, and the practice eats the difference when it does not.
- Records are stored in a format that cannot be produced quickly when a MAC requests them.
Number three is the one that surprises patients. On Medicare's cost page, the Part B deductible is $283, paid once each year, and the patient then usually pays 20% of the cost of each covered service. That split applies only to covered adjustments. For a visit Medicare may deny, such as one that looks like maintenance, the practice can give the Advance Beneficiary Notice of Noncoverage, Form CMS-R-131, before the service; with a proper ABN on file, it may collect the full charge from the patient if Medicare denies the claim. Explain the actual patient responsibility before the first visit, not after the first remittance.
Build the record before the first patient
A record that survives review is assembled at the point of care, not reconstructed later. Three habits do most of the work.
- Write the treatment plan at the initial visit, with the subluxation, the visit count, and the objective measure named.
- Record the same measure at every visit so progress or its absence is visible in the chart.
- Apply the AT modifier per visit, based on what that visit's note shows.
Keep the plan and the notes in one system you can search and export. If a request for records arrives, the practice that can produce a dated plan and matching notes in a day has a different conversation than the one that cannot.
Where the rules come from
Medicare's chiropractic coverage page states the limited benefit and the patient's share: after the Part B deductible, the patient pays 20% of the Medicare-approved amount. Read it as the payer's own statement of what it will pay for. The detailed rules sit in the Medicare Benefit Policy Manual, Chapter 15, section 240, Chiropractic Services.
The CMS billing and coding article for chiropractor services states that coverage is limited and that documentation or medical-necessity gaps can lead to denial. Your MAC's local coverage article is the version that binds your claims, so check the current one for your jurisdiction and note its date.
Accessibility obligations sit outside the payment rules but still apply to a new office. The Department of Justice guide for small businesses covers barrier removal, accessible routes, and service practices for existing facilities, including the readily achievable standard.
Common questions
Does Medicare cover maintenance adjustments?
No. The benefit covers manual manipulation to correct a subluxation, and maintenance therapy is excluded. The AT modifier exists to separate active treatment from maintenance, and a record that cannot show the difference risks denial.
What has to be in the treatment plan?
The subluxation and its level, the planned number of visits, and the objective measure you will track. Record that same measure at each visit so the note shows whether the patient is improving.
What does the patient owe?
For a covered adjustment, the Part B deductible applies first, and the patient then owes coinsurance on the Medicare-approved amount. Services Medicare does not cover are the patient's to pay; tell the patient before the first visit.
Who should review our documentation?
A certified coder familiar with chiropractic coding, plus your MAC for coverage questions and your state board for scope. This article is general business information, not coding, legal, or clinical advice.